IPLab:Lab 7:Bronchogenic Carcinoma: Difference between revisions
Seung Park (talk | contribs) No edit summary |
|||
| (10 intermediate revisions by 2 users not shown) | |||
| Line 2: | Line 2: | ||
This 55-year-old white male had a long history of emphysema and a 60-70 pack-year smoking history. He was in his usual state of health until about one month before admission, at which time he developed increasing dyspnea on exertion. At the same time, his sputum increased from two tablespoons to half a cup of yellow blood-streaked sputum a day. Chest x-ray showed a right hilar mass. Sputum cytology revealed abnormal cells that were "positive for malignancy." He later developed pneumonia and fever. The patient expired soon thereafter. | This 55-year-old white male had a long history of emphysema and a 60-70 pack-year smoking history. He was in his usual state of health until about one month before admission, at which time he developed increasing dyspnea on exertion. At the same time, his sputum increased from two tablespoons to half a cup of yellow blood-streaked sputum a day. Chest x-ray showed a right hilar mass. Sputum cytology revealed abnormal cells that were "positive for malignancy." He later developed pneumonia and fever. The patient expired soon thereafter. | ||
At autopsy significant findings included advanced carcinoma of the right main stem bronchus with extension across the carina to produce obstruction of the left main stem bronchus. There was left lower lobe pneumonia and left upper lobe atelectasis. Extensive metastases were present in regional lymph nodes as well as the pericardium, left atrium, and right kidney. | |||
== Images == | == Images == | ||
| Line 11: | Line 10: | ||
File:IPLab7Bronchogenic3.jpg|This is a photomicrograph of bronchus with ulcerated mucosal surface on the right (1). The submucosa is completely filled with tumor down to the cartilage (2). | File:IPLab7Bronchogenic3.jpg|This is a photomicrograph of bronchus with ulcerated mucosal surface on the right (1). The submucosa is completely filled with tumor down to the cartilage (2). | ||
File:IPLab7Bronchogenic4.jpg|This is a higher-power photomicrograph of bronchus with the ulcerated mucosal surface on the right and tumor underneath. | File:IPLab7Bronchogenic4.jpg|This is a higher-power photomicrograph of bronchus with the ulcerated mucosal surface on the right and tumor underneath. | ||
File: | File:IPLab7Bronchogenic5x.jpg|This is a higher-power photomicrograph showing cytologic detail of the tumor cells with foci of keratin pearl formation (arrows). | ||
File:IPLab7Bronchogenic6b.jpg|This is a high power photomicrograph of tumor cells with more keratin production. | |||
File:IPLab7Bronchogenic8b.jpg|This high-power photomicrograph of tumor shows the keratin production and areas of necrosis (N). | |||
File: | |||
File: | |||
</gallery> | </gallery> | ||
== Virtual Microscopy == | |||
<peir-vm>IPLab7Bronchogenic</peir-vm> | |||
== Study Questions == | == Study Questions == | ||
| Line 32: | Line 32: | ||
# serotonin, associated with the carcinoid syndrome. The incidence of clinically significant syndromes related to these factors ranges from 1 to 10% of all lung cancer patients. Any one of the histologic types of tumors may occasionally produce any one of the hormones, but tumors producing ACTH and ADH are predominantly small cell carcinomas and those producing hypercalcemia are mostly squamous cell tumors.</spoiler> | # serotonin, associated with the carcinoid syndrome. The incidence of clinically significant syndromes related to these factors ranges from 1 to 10% of all lung cancer patients. Any one of the histologic types of tumors may occasionally produce any one of the hormones, but tumors producing ACTH and ADH are predominantly small cell carcinomas and those producing hypercalcemia are mostly squamous cell tumors.</spoiler> | ||
* <spoiler text="What is the prognosis for patients with bronchiogenic carcinoma?">The clinical course is somewhat variable but in general the prognosis is poor with a 5 year survival of approximately 9%.</spoiler> | * <spoiler text="What is the prognosis for patients with bronchiogenic carcinoma?">The clinical course is somewhat variable but in general the prognosis is poor with a 5 year survival of approximately 9%.</spoiler> | ||
== Additional Resources == | |||
=== Reference === | |||
* [http://emedicine.medscape.com/article/279960-overview eMedicine Medical Library: Non-Small Cell Lung Cancer] | |||
* [http://emedicine.medscape.com/article/1689988-overview eMedicine Medical Library: Genetics of Non-Small Cell Lung Cancer] | |||
* [http://emedicine.medscape.com/article/280104-overview eMedicine Medical Library: Small Cell Lung Cancer] | |||
* [http://www.merckmanuals.com/professional/pulmonary_disorders/tumors_of_the_lungs/lung_carcinoma.html Merck Manual: Lung Carcinoma] | |||
=== Journal Articles === | |||
* Hyer JD, Silvestri G. [http://www.ncbi.nlm.nih.gov/pubmed/10763092 Diagnosis and staging of lung cancer]. ''Clin Chest Med'' 2000 Mar;21(1):95-106, viii-ix. | |||
=== Images === | |||
* [{{SERVER}}/library/index.php?/tags/27-lung/112-carcinoma PEIR Digital Library: Lung Carcinoma Images] | |||
* [http://library.med.utah.edu/WebPath/LUNGHTML/LUNGIDX.html WebPath: Pulmonary Pathology] | |||
== Related IPLab Cases == | |||
* [[IPLab:Lab 7:Lip SCC|Lab 7: Lip: Squamous Cell Carcinoma]] | |||
* [[IPLab:Lab 7:Esophagus SCC|Lab 7: Esophagus: Squamous Cell Carcinoma]] | |||
* [[IPLab:Lab 7:IDC|Lab 7: Breast: Infiltrating Ductal Carcinoma]] | |||
* [[IPLab:Lab 7:Adenocarcinoma|Lab 7: Colon: Adenocarcinoma]] | |||
* [[IPLab:Lab 7:Metastatic Adenocarcinoma|Lab 7: Lung & Liver: Metastatic Adenocarcinoma]] | |||
{{IPLab 7}} | {{IPLab 7}} | ||
[[Category: IPLab:Lab 7]] | [[Category: IPLab:Lab 7]] | ||
Latest revision as of 22:05, 8 July 2020
Clinical Summary
This 55-year-old white male had a long history of emphysema and a 60-70 pack-year smoking history. He was in his usual state of health until about one month before admission, at which time he developed increasing dyspnea on exertion. At the same time, his sputum increased from two tablespoons to half a cup of yellow blood-streaked sputum a day. Chest x-ray showed a right hilar mass. Sputum cytology revealed abnormal cells that were "positive for malignancy." He later developed pneumonia and fever. The patient expired soon thereafter.
At autopsy significant findings included advanced carcinoma of the right main stem bronchus with extension across the carina to produce obstruction of the left main stem bronchus. There was left lower lobe pneumonia and left upper lobe atelectasis. Extensive metastases were present in regional lymph nodes as well as the pericardium, left atrium, and right kidney.
Images
-
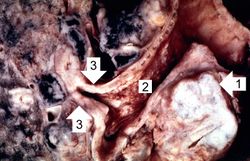 This is a gross photograph of bronchogenic carcinoma. The large tumor mass can be seen adjacent to the bronchus (1). Note that the epithelial surface of the bronchus is rough and irregular (2). The first branch off the right main stem bronchus is partially occluded by the thickened mucosa and submucosa (3).
-
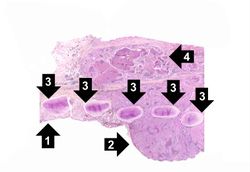 This is a low-power photomicrograph of bronchus showing normal mucosa (1) with transition to carcinoma (2). Note the bronchial cartilage (3) and the invasion of tumor through the entire wall of the bronchus with tumor extending to the serosal surface (4).
-
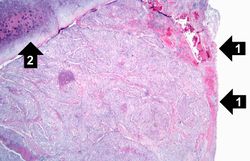 This is a photomicrograph of bronchus with ulcerated mucosal surface on the right (1). The submucosa is completely filled with tumor down to the cartilage (2).
-
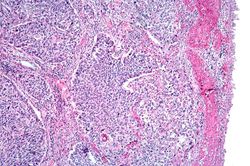 This is a higher-power photomicrograph of bronchus with the ulcerated mucosal surface on the right and tumor underneath.
-
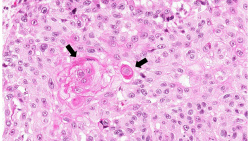 This is a higher-power photomicrograph showing cytologic detail of the tumor cells with foci of keratin pearl formation (arrows).
-
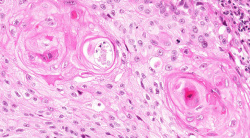 This is a high power photomicrograph of tumor cells with more keratin production.
-
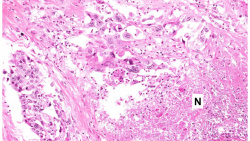 This high-power photomicrograph of tumor shows the keratin production and areas of necrosis (N).


Virtual Microscopy
Study Questions
Additional Resources
Reference
- eMedicine Medical Library: Non-Small Cell Lung Cancer
- eMedicine Medical Library: Genetics of Non-Small Cell Lung Cancer
- eMedicine Medical Library: Small Cell Lung Cancer
- Merck Manual: Lung Carcinoma
Journal Articles
- Hyer JD, Silvestri G. Diagnosis and staging of lung cancer. Clin Chest Med 2000 Mar;21(1):95-106, viii-ix.
Images
Related IPLab Cases
- Lab 7: Lip: Squamous Cell Carcinoma
- Lab 7: Esophagus: Squamous Cell Carcinoma
- Lab 7: Breast: Infiltrating Ductal Carcinoma
- Lab 7: Colon: Adenocarcinoma
- Lab 7: Lung & Liver: Metastatic Adenocarcinoma