IPLab:Lab 5:Nodular Intercapillary Glomerulosclerosis: Difference between revisions
Seung Park (talk | contribs) No edit summary |
Seung Park (talk | contribs) No edit summary |
||
| Line 20: | Line 20: | ||
* <spoiler text="What material is found within these sclerotic nodules and what happens to these lesions over time?">The Kimmelstiel-Wilson (K-W) lesions are ovoid or spherical, often laminated, hyaline masses situated in the periphery of the glomerulus. They are usually within the mesangium of the glomeruli. The nodules are composed of lipids and fibrin. As the disease progresses the K-W nodules enlarge until they compress and obliterate the glomerular tuft. Because of these glomerular and arteriolar lesions, the blood flow to the kidney is compromised and the kidney becomes ischemic. This results in tubular atrophy and interstitial fibrosis and leads to a roughened renal cortical surface.</spoiler> | * <spoiler text="What material is found within these sclerotic nodules and what happens to these lesions over time?">The Kimmelstiel-Wilson (K-W) lesions are ovoid or spherical, often laminated, hyaline masses situated in the periphery of the glomerulus. They are usually within the mesangium of the glomeruli. The nodules are composed of lipids and fibrin. As the disease progresses the K-W nodules enlarge until they compress and obliterate the glomerular tuft. Because of these glomerular and arteriolar lesions, the blood flow to the kidney is compromised and the kidney becomes ischemic. This results in tubular atrophy and interstitial fibrosis and leads to a roughened renal cortical surface.</spoiler> | ||
* <spoiler text="What percent of diabetics develop this lesion and what are the functional consequences?">Approximately 15-30% of long term diabetics develop K-W lesions and in most instances it is associated with renal failure.</spoiler> | * <spoiler text="What percent of diabetics develop this lesion and what are the functional consequences?">Approximately 15-30% of long term diabetics develop K-W lesions and in most instances it is associated with renal failure.</spoiler> | ||
== Additional Resources == | |||
=== Reference === | |||
* [http://emedicine.medscape.com/article/117739-overview eMedicine Medical Library: Type 1 Diabetes Mellitus] | |||
* [http://emedicine.medscape.com/article/117853-overview eMedicine Medical Library: Type 2 Diabetes Mellitus] | |||
* [http://www.merckmanuals.com/professional/endocrine_and_metabolic_disorders/diabetes_mellitus_and_disorders_of_carbohydrate_metabolism/diabetes_mellitus_dm.html Merck Manual: Diabetes Mellitus (DM)] | |||
=== Journal Articles === | |||
* Herzenberg AM, Holden JK, Singh S, Magil AB. [http://www.ncbi.nlm.nih.gov/pubmed/10469869 Idiopathic nodular glomerulosclerosis]. ''Am J Kidney Dis'' 1999 Sep;34(3):560-4. | |||
=== Images === | |||
* [http://peir.path.uab.edu/library/index.php?/tags/137-diabetic_glomerulosclerosis PEIR Digital Library: Diabetic Glomerulosclerosis Images] | |||
* [http://library.med.utah.edu/WebPath/RENAHTML/RENALIDX.html#3 WebPath: Interstitial Diseases of the Kidney] | |||
== Related IPLab Cases == | |||
* [[IPLab:Lab 1:Kidney Infarction|Lab 1: Kidney: Infarction (Coagulative Necrosis)]] | |||
{{IPLab 5}} | {{IPLab 5}} | ||
[[Category: IPLab:Lab 5]] | [[Category: IPLab:Lab 5]] | ||
Revision as of 15:58, 22 August 2013
Clinical Summary
This 57-year-old white male with a 25-year history of Type I diabetes mellitus (insulin-dependent ) developed an acute myocardial infarction followed by cerebral infarction, pulmonary dysfunction, and renal failure. There was a history of hypertension and proteinuria. Laboratory findings included a BUN and creatinine of 69 mg/dL and 3.3 mg/dL which subsequently rose to 113 and 4.8, respectively. He subsequently died of multisystem failure.
Autopsy Findings
The autopsy showed the expected left ventricular hypertrophy, a large acute myocardial infarction, and a large right cerebral infarction. The pancreas showed amyloidosis of the islets. There was extensive atherosclerosis and arteriolosclerosis. The kidneys were large, weighing 220 and 240 grams respectively, and had smooth glistening surfaces, a few cortical scars, and blurring of the corticomedullary junctions.
Images
-
 This is a gross photograph of the kidneys from this case. Note that there are multiple shrunken regions (old infarcts) (arrows) and the kidneys have a rough granular appearance on the surface, which is caused by multiple small infarcts of small vessels throughout the cortex.
-
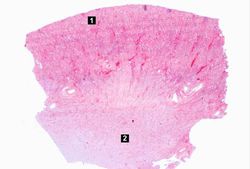 This is a low-power photomicrograph of the kidney from this patient. The section extends from cortex (1) to the medulla (2).
-
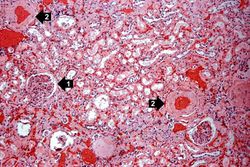 This is a higher-power photomicrograph of the cortical region. In this region there is ischemic obsolescence of glomeruli and one glomerulus with nodular glomerulosclerosis (1). Also note the thickened walls of the blood vessels (2).
-
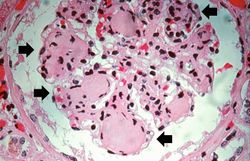
 This is a high-power photomicrograph of two glomeruli with intercapillary glomerulosclerosis (arrows).
-
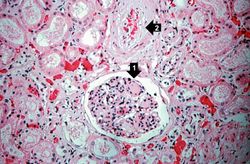 This is a photomicrograph of a glomerulus with nodular glomerulosclerosis (1). Also note the intertubular fibrosis and the changes in the blood vessels (2).
-
-
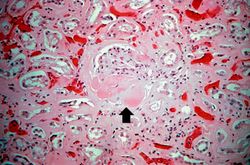 This is a photomicrograph of kidney with a focal exudative lesion in a glomerulus (arrow) and sclerosis, interstitial fibrosis, and congestion.


Study Questions
Additional Resources
Reference
- eMedicine Medical Library: Type 1 Diabetes Mellitus
- eMedicine Medical Library: Type 2 Diabetes Mellitus
- Merck Manual: Diabetes Mellitus (DM)
Journal Articles
- Herzenberg AM, Holden JK, Singh S, Magil AB. Idiopathic nodular glomerulosclerosis. Am J Kidney Dis 1999 Sep;34(3):560-4.
Images
- PEIR Digital Library: Diabetic Glomerulosclerosis Images
- WebPath: Interstitial Diseases of the Kidney
Related IPLab Cases
| |||||