IPLab:Lab 3:Acute Myocardial Infarction: Difference between revisions
Seung Park (talk | contribs) Created page with "== Images == <gallery heights="250px" widths="250px"> File:IPLab3AcuteMyocardialInfarction1.jpg|This is a low-power photomicrograph of infarcted heart. There is a layer of sur..." |
Seung Park (talk | contribs) No edit summary |
||
| Line 1: | Line 1: | ||
== Clinical Summary == | |||
This 78-year-old male experienced a posterior myocardial infarction six years prior to this admission. Recently, he had begun to experience occasional angina. Four days prior to death, he experienced anterior chest pain and discomfort which he regarded as not too distressing. However, EKGs showed a classic acute anterior myocardial infarction in addition to the healed posterior infarct. The patient progressively deteriorated with left ventricular failure and died with arrhythmias and pulmonary edema. Pertinent laboratory data are: | |||
# Aspartate Aminotransferase (AST) 60 IU/L. | |||
# Total Creatine Phosphokinase (CPK) 165 IU/L. All of the activity was due to CPK III (MM) isoenzyme fraction; no CPK (MB) activity was detectable. | |||
# Lactic Dehydrogenase (LDH) 720 IU/L. LD1 fraction was greater than LD2. | |||
== Autopsy Findings == | |||
Examination of the heart showed a healed posterior infarct. The right coronary artery was completely occluded but partially recanalized. The left main coronary artery had severe atherosclerotic stenosis and a thrombus filling the lumen. The entire anterolateral aspect of the left ventricle was soft with variegated areas appearing hyperemic or pale. There was extensive mural thrombosis and reactive pericarditis. | |||
== Images == | == Images == | ||
<gallery heights="250px" widths="250px"> | <gallery heights="250px" widths="250px"> | ||
Revision as of 23:47, 18 August 2013
Clinical Summary
This 78-year-old male experienced a posterior myocardial infarction six years prior to this admission. Recently, he had begun to experience occasional angina. Four days prior to death, he experienced anterior chest pain and discomfort which he regarded as not too distressing. However, EKGs showed a classic acute anterior myocardial infarction in addition to the healed posterior infarct. The patient progressively deteriorated with left ventricular failure and died with arrhythmias and pulmonary edema. Pertinent laboratory data are:
- Aspartate Aminotransferase (AST) 60 IU/L.
- Total Creatine Phosphokinase (CPK) 165 IU/L. All of the activity was due to CPK III (MM) isoenzyme fraction; no CPK (MB) activity was detectable.
- Lactic Dehydrogenase (LDH) 720 IU/L. LD1 fraction was greater than LD2.
Autopsy Findings
Examination of the heart showed a healed posterior infarct. The right coronary artery was completely occluded but partially recanalized. The left main coronary artery had severe atherosclerotic stenosis and a thrombus filling the lumen. The entire anterolateral aspect of the left ventricle was soft with variegated areas appearing hyperemic or pale. There was extensive mural thrombosis and reactive pericarditis.
Images
-
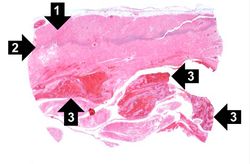 This is a low-power photomicrograph of infarcted heart. There is a layer of surviving myocardial tissue (1) along the epicardium and then a blue line (2) which represents the accumulation of inflammatory cells at the border of the infarct. There is thrombotic material (3) adherent to the endocardial surface.
-
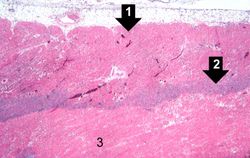 This is a higher-power photomicrograph which shows more clearly the viable tissue along the epicardium (1), the blue line of inflammatory cells (2), and the infarcted myocardium (3).
-
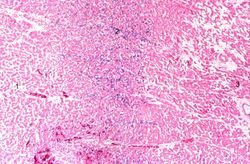 This is a photomicrograph of the edge of the infarct with normal tissue on the left (1). The accumulation of inflammatory cells (2) is at the edge of the infarcted tissue (3).
-
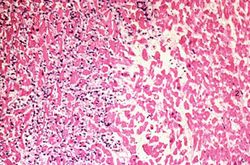 This is a higher-power photomicrograph of the edge of the infarct. The accumulation of inflammatory cells is on the left (1) and the infarcted tissue is on the right (2). Note that intact cells can be seen in the infarct but there are no nuclei.
-
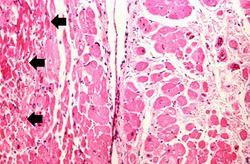 This is a high-power photomicrograph of another area of this section. There are several hypereosinophilic cells within this section (arrows).
-
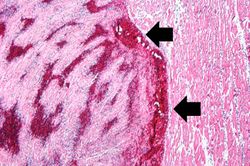 This is a low-power photomicrograph of a mural thrombus (1) adherent to the endocardial surface (arrows).
-
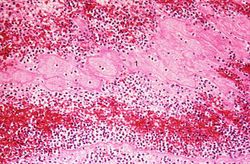 This is a photomicrograph of the lines of Zahn. Pale areas (1) represent platelets with some fibrin and the darker lines (2) represent RBCs and leukocytes enmeshed in fibrin strands.


