IPLab:Lab 4:Mural Thrombus: Difference between revisions
No edit summary |
|||
| (10 intermediate revisions by 2 users not shown) | |||
| Line 1: | Line 1: | ||
== Clinical Summary == | == Clinical Summary == | ||
This 67-year-old female was transferred to the hospital from a nursing home in a comatose state. Physical findings on examination were compatible with brain stem infarction. On the fourth hospital day, an electrocardiogram revealed changes compatible with anterior myocardial infarction. The patient remained comatose with quadriplegia and expired on the 16th hospital day. | |||
Examination of the brain revealed extensive infarction involving the midbrain and cerebellum with complete occlusion of the upper one-half of the basilar artery; there was also extensive coronary artery atherosclerosis. A large aneurysm of the left ventricle was present; this was filled with mural thrombus. Extensive infarction of the lateral and posterior portions of the left ventricular wall toward the base of the heart was also found. | |||
Examination of the brain revealed extensive infarction involving the midbrain and cerebellum with complete occlusion of the upper one-half of the basilar artery; there was also extensive coronary artery atherosclerosis. A large aneurysm of the left ventricle was present; this was filled with mural thrombus. Extensive infarction of the lateral and posterior portions of the left ventricular wall toward the base of the heart was also found. | |||
== Images == | == Images == | ||
| Line 17: | Line 14: | ||
File:IPLab4MuralThrombus7.jpg|This high-power photomicrograph of thrombus demonstrates more clearly the components of the layers--the pale regions which contain primarily platelets (degranulated platelets) with some fibrin (1), and the red areas which contain RBCs, some leukocytes, and fibrin (2). | File:IPLab4MuralThrombus7.jpg|This high-power photomicrograph of thrombus demonstrates more clearly the components of the layers--the pale regions which contain primarily platelets (degranulated platelets) with some fibrin (1), and the red areas which contain RBCs, some leukocytes, and fibrin (2). | ||
</gallery> | </gallery> | ||
== Virtual Microscopy == | |||
=== Heart:Mural Thrombus === | |||
<peir-vm>IPLab4MuralThrombus</peir-vm> | |||
=== Normal Heart === | |||
<peir-vm>IPLab2Hypertrophy_normal_Heart</peir-vm> | |||
== Study Questions == | |||
* <spoiler text="Why do mural thrombi form on the endocardium of the heart after a myocardial infarction?">The infarct produced necrosis and inflammation. Also, the infarcted ventricular wall is akinetic and/or dyskinetic (bulges outward during systole). Thus, the blood in the ventricle tends to form thrombi on the surface of the infarcted endocardium.</spoiler> | |||
* <spoiler text="List the sequence of events leading to mural thrombus formation.">* Platelets bind to damage endocardium and release ADP, 5-HT, thromboxane and platelet factor 4. | |||
* This results in recruitment of more platelets and more degranulation of platelets with activation of the clotting cascade. | |||
* Thrombin is activated leading to fibrin polymerization. | |||
* This process results in the development of a platelet-fibrin thrombus.</spoiler> | |||
* <spoiler text="What are possible sequelae of these mural thrombi?">The thrombotic material may break off and go to the brain or kidney (the two most likely sites since they get so much blood flow) or any arterial system.</spoiler> | |||
== Additional Resources == | |||
=== Reference === | |||
* [http://emedicine.medscape.com/article/1950759-overview eMedicine Medical Library: Noncoronary Atherosclerosis] | |||
* [http://emedicine.medscape.com/article/155919-overview eMedicine Medical Library: Myocardial Infarction] | |||
* [http://www.merckmanuals.com/professional/hematology_and_oncology/thrombotic_disorders/thrombotic_disorders.html Merck Manual: Thrombotic Disorders] | |||
* [http://www.merckmanuals.com/professional/cardiovascular_disorders/coronary_artery_disease/acute_coronary_syndromes_acs.html Merck Manual: Acute Coronary Syndromes (ACS)] | |||
=== Journal Articles === | |||
* Diop D, Aghababian RV. [http://www.ncbi.nlm.nih.gov/pubmed/11373977 Definition, classification, and pathophysiology of acute coronary ischemic syndromes]. ''Emerg Med Clin North Am'' 2001 May;19(2):259-67. | |||
=== Images === | |||
* [{{SERVER}}/library/index.php?/tags/424-mural_thrombus PEIR Digital Library: Mural Thrombus Images] | |||
* [http://library.med.utah.edu/WebPath/CVHTML/CVIDX.html#3 WebPath: Myocardial Infarction] | |||
* [http://library.med.utah.edu/WebPath/CVHTML/CVIDX.html#2 WebPath: Atherosclerotic Cardiovascular Disease] | |||
== Related IPLab Cases == | |||
* [[IPLab:Lab 1:Myocardial Infarction|Lab 1: Heart: Myocardial Infarction (Coagulative Necrosis)]] | |||
* [[IPLab:Lab 3:Acute Myocardial Infarction|Lab 3: Heart: Acute Myocardial Infarction]] | |||
* [[IPLab:Lab 3:Healed Myocardial Infarction|Lab 3: Heart: Healed Myocardial Infarction]] | |||
* [[IPLab:Lab 4:Thrombosis|Lab 4: Coronary Artery: Thrombosis]] | |||
* [[IPLab:Lab 4:Pulmonary Congestion and Edema|Lab 4: Lung: Pulmonary Congestion and Edema]] | |||
{{IPLab 4}} | {{IPLab 4}} | ||
[[Category: IPLab:Lab 4]] | [[Category: IPLab:Lab 4]] | ||
Latest revision as of 20:57, 23 June 2020
Clinical Summary
This 67-year-old female was transferred to the hospital from a nursing home in a comatose state. Physical findings on examination were compatible with brain stem infarction. On the fourth hospital day, an electrocardiogram revealed changes compatible with anterior myocardial infarction. The patient remained comatose with quadriplegia and expired on the 16th hospital day.
Examination of the brain revealed extensive infarction involving the midbrain and cerebellum with complete occlusion of the upper one-half of the basilar artery; there was also extensive coronary artery atherosclerosis. A large aneurysm of the left ventricle was present; this was filled with mural thrombus. Extensive infarction of the lateral and posterior portions of the left ventricular wall toward the base of the heart was also found.
Images
-
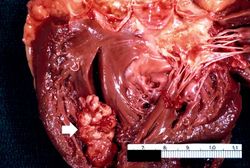 This is a gross photograph of the heart from this case demonstrating the well-formed thrombus (arrow) tightly attached to the myocardium near the apex of the left ventricle.
-
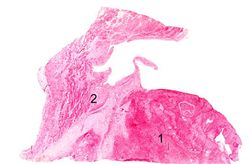 This is a low-power photomicrograph of the thrombus (1) attached to the myocardium (2).
-
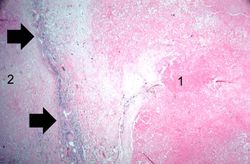 This higher-power photomicrograph shows the border between the thrombus on the right (1) and the endocardium on the left (2). There is a line of inflammatory cells at this interface (arrow).
-
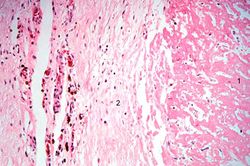 This is a high-power photomicrograph of the border zone between the thrombus (1) and the endocardium (2). In this region there is less inflammation at the border zone.
-
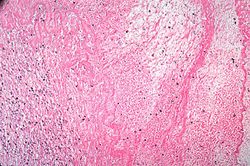 This photomicrograph illustrates the layered effect of the thrombus.
-
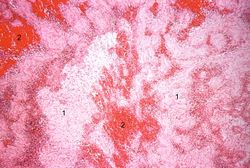 This is a higher-power photomicrograph of the thrombus. Note the pale regions which contain primarily platelets (degranulated platelets) with some fibrin (1), and the red areas which contain RBCs, some leukocytes, and fibrin(2).
-
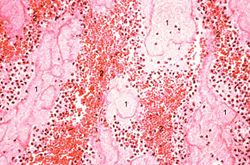 This high-power photomicrograph of thrombus demonstrates more clearly the components of the layers--the pale regions which contain primarily platelets (degranulated platelets) with some fibrin (1), and the red areas which contain RBCs, some leukocytes, and fibrin (2).


Virtual Microscopy
Heart:Mural Thrombus
Normal Heart
Study Questions
Additional Resources
Reference
- eMedicine Medical Library: Noncoronary Atherosclerosis
- eMedicine Medical Library: Myocardial Infarction
- Merck Manual: Thrombotic Disorders
- Merck Manual: Acute Coronary Syndromes (ACS)
Journal Articles
- Diop D, Aghababian RV. Definition, classification, and pathophysiology of acute coronary ischemic syndromes. Emerg Med Clin North Am 2001 May;19(2):259-67.
Images
- PEIR Digital Library: Mural Thrombus Images
- WebPath: Myocardial Infarction
- WebPath: Atherosclerotic Cardiovascular Disease
Related IPLab Cases
- Lab 1: Heart: Myocardial Infarction (Coagulative Necrosis)
- Lab 3: Heart: Acute Myocardial Infarction
- Lab 3: Heart: Healed Myocardial Infarction
- Lab 4: Coronary Artery: Thrombosis
- Lab 4: Lung: Pulmonary Congestion and Edema
| |||||