Renal Pathology: Difference between revisions
No edit summary |
No edit summary |
||
| Line 1: | Line 1: | ||
== Renal Pathology Virtual Microscopy Study Set == | == Renal Pathology Virtual Microscopy Study Set == | ||
'''Renal Pathology Cases.''' These renal pathology cases were collected by William Cook, M.D., PhD as a teaching set for use by UAB pathology residents interested in renal pathology. Virtual Microscopy slides were curated and made available on PEIR by Dr. Peter Anderson and Bade Iriabho. | '''Renal Pathology Cases.''' These renal pathology cases were collected by William Cook, M.D., PhD as a teaching set for use by UAB pathology residents interested in renal pathology. Virtual Microscopy slides were curated and made available on PEIR by Dr. Peter Anderson and Bade Iriabho. | ||
=='''Case RP-001'''== | |||
== Clinical History== | |||
The patient is a 76 year old female. | |||
Recently detected renal insufficiency, proteinuria and hypertension. BUN 50, creatinine 2.6, creatinine clearance 36 ml/min, urinary protein 3.5 g/24 hr. BP 150/90. | |||
===Gross Description:=== | |||
Received in Zeus fixative is one core of renal tissue measuring 1.1 cm in length. This is entirely submitted for immunofluorescence. Received in Carson's fixative are two cores of tissue measuring 8 mm each. Two 1-mm fragments are taken for EM, and the remaining tissue is processed for light microscopy. | |||
==Pathology== | |||
<gallery heights="250px" widths="250px"> | |||
CytologicallyYoursCoW20131125Cytology1.jpg|4x magnification of the specimen. We see colloid, few small clusters of cells macrophages, and scattered cells in the background. | |||
CytologicallyYoursCoW20131125Cytology2.jpg|20x magnification. Colloid is present at the bottom of the field. There are single cells in the background and small groups of cells. | |||
CytologicallyYoursCoW20131125Cytology3.jpg|40x magnification of a large multinucleated giant cell. There is colloid and macrophages present in the background. | |||
CytologicallyYoursCoW20131125Cytology4.jpg|10x magnification. Here we have a large cohesive group of spindled epithelioid cells. The centers are non-necrotizing. In the background there is colloid and single cells present. | |||
CytologicallyYoursCoW20131125Cytology5.jpg|10x magnification. Here there are more groups of cohesive epithleioid spindled cells with non-necrotizing centers. | |||
CytologicallyYoursCoW20131125Cytology6.jpg|40x magnification of a group of cohesive epithelioid spindled cells with non-necrotizing center. | |||
</gallery> | |||
===Resident Questions=== | |||
* <spoiler text="Benign or malignant?"> | |||
These groups of cohesive spindled epithelioid cells are also known as granulomas. Granulomatous thyroiditis is a benign entity. | |||
</spoiler> | |||
* <spoiler text="With these cytologic findings what should be included in our differential diagnosis?"> | |||
When we see granulomas in a thyroid we should always think of an infectious process, sarcoidosis, Hashimoto's thyroiditis, palpation thyroiditis, and granulomatous thyroiditis. The other entity that you should think of when you see epithelioid giant cells is papillary thyroid carcinoma. | |||
</spoiler> | |||
<div class="usermessage mw-customtoggle-diagnosis" style="cursor:pointer"> Click here to toggle the diagnosis and case discussion.</div> | |||
<div class="mw-collapsible mw-collapsed" id="mw-customcollapsible-diagnosis"> | |||
<div class="mw-collapsible-content"> | |||
==Diagnosis== | |||
===Cytology=== | |||
'''Benign aspirate, see comment'''. | |||
'''COMMENT''': | |||
'''There are non-necrotizing granulomas, benign follicular cells, macrophages, colloid, lymphocytes, and multinucleated giant cells; consistent with granulomatous thyroiditis'''. | |||
==Case Discussion== | |||
Granulomatous Thyroiditis is also known as deQuervain or subacute thyroiditis. It is a postviral syndrome. Usual presentation is in a young woman who has just gotten over a cold. | |||
Patients present with painful thyroid, fever, fatigue, chills. Diagnosis is usually made clinically, therefore FNA biopsy is usually not performed. The disease is usually self-limiting. | |||
If an aspirate is performed it may be scantly cellular due to pain and fibrosis. If material is gathered you may see non-caseating granulomas, colloid, chronic inflammation, and multinucleated giant cells. | |||
</div></div> | |||
{{Cytologically Yours}} | |||
[[Category: Case Reports]] | |||
Revision as of 16:13, 3 October 2026
Renal Pathology Virtual Microscopy Study Set
Renal Pathology Cases. These renal pathology cases were collected by William Cook, M.D., PhD as a teaching set for use by UAB pathology residents interested in renal pathology. Virtual Microscopy slides were curated and made available on PEIR by Dr. Peter Anderson and Bade Iriabho.
Case RP-001
Clinical History
The patient is a 76 year old female.
Recently detected renal insufficiency, proteinuria and hypertension. BUN 50, creatinine 2.6, creatinine clearance 36 ml/min, urinary protein 3.5 g/24 hr. BP 150/90.
Gross Description:
Received in Zeus fixative is one core of renal tissue measuring 1.1 cm in length. This is entirely submitted for immunofluorescence. Received in Carson's fixative are two cores of tissue measuring 8 mm each. Two 1-mm fragments are taken for EM, and the remaining tissue is processed for light microscopy.
Pathology
-
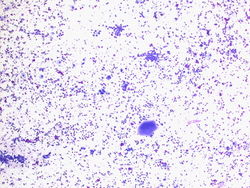 4x magnification of the specimen. We see colloid, few small clusters of cells macrophages, and scattered cells in the background.
-
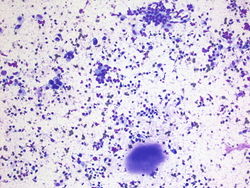 20x magnification. Colloid is present at the bottom of the field. There are single cells in the background and small groups of cells.
-
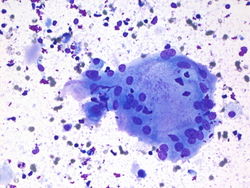 40x magnification of a large multinucleated giant cell. There is colloid and macrophages present in the background.
-
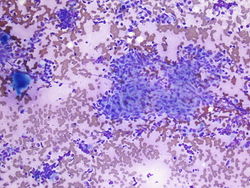 10x magnification. Here we have a large cohesive group of spindled epithelioid cells. The centers are non-necrotizing. In the background there is colloid and single cells present.
-
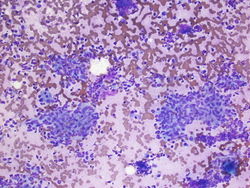 10x magnification. Here there are more groups of cohesive epithleioid spindled cells with non-necrotizing centers.
-
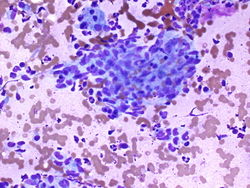 40x magnification of a group of cohesive epithelioid spindled cells with non-necrotizing center.


Resident Questions
Diagnosis
Cytology
Benign aspirate, see comment.
COMMENT: There are non-necrotizing granulomas, benign follicular cells, macrophages, colloid, lymphocytes, and multinucleated giant cells; consistent with granulomatous thyroiditis.
Case Discussion
Granulomatous Thyroiditis is also known as deQuervain or subacute thyroiditis. It is a postviral syndrome. Usual presentation is in a young woman who has just gotten over a cold.
Patients present with painful thyroid, fever, fatigue, chills. Diagnosis is usually made clinically, therefore FNA biopsy is usually not performed. The disease is usually self-limiting.
If an aspirate is performed it may be scantly cellular due to pain and fibrosis. If material is gathered you may see non-caseating granulomas, colloid, chronic inflammation, and multinucleated giant cells.
| ||||||||